When a patient comes to me worried that their rhinoplasty has been botched, the first thing I want to understand is what they are seeing, what they are feeling and how long it has been since their surgery.
Not every rhinoplasty that looks wrong during recovery has failed. Swelling, temporary asymmetry and changes in the nasal tip can continue for months. But there are also situations where the original surgery has weakened the structural support of the nose, created breathing problems or produced an appearance that will not improve simply by waiting.
The term “botched rhinoplasty” can describe several very different problems. Some patients are unhappy with the appearance of an otherwise functional nose. Others have genuine anatomical problems that require reconstruction.
Before I can tell someone whether revision surgery makes sense, I need to understand what actually went wrong and whether another operation can realistically improve it.
HEALING OR A STRUCTURAL PROBLEM?
Is Your Rhinoplasty Botched, or Is Your Nose Still Healing?
Rhinoplasty recovery takes longer than most patients expect. The splint may come off within the first couple of weeks, but the nose has not reached its final shape at that point.
Swelling can persist for months, particularly around the nasal tip. Scar tissue continues to mature and subtle changes can occur throughout the first year and sometimes longer.
That is why I am cautious about labeling an early result a surgical failure.
However, certain changes deserve a closer examination, especially when they persist or become progressively more noticeable.
Changes in Nasal Shape
A nose that becomes increasingly crooked, pinched, collapsed, or unusually shortened may have lost some of its underlying structural support. This can happen when cartilage has been excessively removed, weakened, or repositioned in a way that no longer provides adequate stability. As healing progresses and swelling subsides, these structural problems may become more noticeable rather than less. The nasal tip may begin to droop, the bridge may develop an irregular contour, or the nostrils may appear increasingly asymmetrical.
One of the things I look for is whether the change is caused by normal postoperative swelling or by an actual deficiency in the nasal framework. Swelling can temporarily distort the appearance of the nose, but it does not explain every persistent irregularity. When the underlying cartilage or bone has been altered in a way that compromises support, the problem may not resolve with additional healing. Identifying that distinction is essential before I can determine whether revision rhinoplasty would be appropriate.
Breathing Problems
Some nasal congestion is expected after rhinoplasty as swelling temporarily narrows the airway. However, persistent or worsening breathing difficulties may indicate a structural problem involving the septum, nasal valves, or supporting cartilage. These concerns deserve closer evaluation, particularly when breathing does not improve as healing progresses.
I pay particular attention to patients who breathe comfortably before surgery but develop new obstruction afterward. In some cases, excessive cartilage removal or weakened nasal valves can cause the airway to narrow during breathing. Identifying the source of that obstruction helps me determine whether additional healing is needed or structural correction should be considered.
Persistent Asymmetry or Tip Problems
Some asymmetry during rhinoplasty recovery is normal, particularly while swelling is resolving. However, a persistently distorted nasal tip, uneven nostrils, or visible collapse may indicate that the underlying cartilage is not providing adequate support. These changes can become more noticeable as swelling decreases and the final nasal contours begin to emerge.
When evaluating these concerns, I look at the position, strength, and symmetry of the remaining tip cartilage. Excessive cartilage removal or inadequate support can contribute to a pinched, drooping, or uneven appearance. Understanding whether the problem is related to healing or structural weakness helps me determine if revision surgery may be beneficial.
THE UNDERLYING ANATOMY
Why a Rhinoplasty Can Fail

The septum provides central support for the nose. I often describe it as the tentpole that helps maintain the structure around it.
If too much septal cartilage or other supporting cartilage is removed during the original operation, the remaining framework may no longer have enough strength to maintain its intended shape.
Over time, this can contribute to a crooked, collapsed, pinched or otherwise distorted appearance. It can also affect the internal nasal airway.
That is why preserving structural support is so important in primary rhinoplasty, and why rebuilding that support can become the central challenge during revision surgery.
What Causes an Unsuccessful Rhinoplasty?
There is not one explanation that applies to every patient. When I examine a nose after previous surgery, I look at the relationship between the remaining cartilage, nasal bones, skin, scar tissue and airway.
Too Much Cartilage Was Removed
One of the most common structural problems I encounter in my own revision practice is excessive removal of septal cartilage during the original operation.
In my experience, approximately 75% of the revision cases I evaluate involve excessive septal cartilage removal as an important contributing factor. That is an observation from my practice, not a published national statistic.
When the septum has been weakened, the surrounding structures may gradually lose their support. The problem is no longer simply how the nose looks. It is whether the framework can maintain the desired shape.
The Nasal Tip Was Over-Reduced
The nasal tip depends on a delicate arrangement of cartilage and soft tissue to maintain its shape and position. When too much cartilage is removed during rhinoplasty, the tip can lose the support needed to maintain a natural contour. This may result in a pinched appearance, excessive upward rotation, asymmetry, or a loss of definition that becomes more apparent as swelling subsides.
In revision rhinoplasty, I evaluate how much of the original tip cartilage remains and whether the supporting structures are stable. Sometimes the problem can be corrected by repositioning existing cartilage, while other cases require grafts to rebuild support. My goal is to restore a balanced, natural-looking tip without creating additional weakness in the nasal framework.
Scar Tissue Changed the Shape
Every rhinoplasty creates scar tissue. In some patients, scar contraction can influence the contour of the nose or place pressure on the remaining cartilage.
This becomes especially important in revision surgery because I am operating through tissues that have already healed from a previous procedure.
The Nasal Airway Was Compromised
A nose may look relatively normal externally while functioning poorly internally. Weakness of the nasal valves, changes to the septum or inadequate support can contribute to persistent breathing obstruction.
I do not consider a revision successful if I improve the appearance while ignoring a significant functional problem.
A Previous Implant Developed Problems
Some patients come to me after rhinoplasty involving synthetic implants, including procedures performed many years earlier.
Implants can sometimes develop problems involving displacement, infection, contour irregularity or thinning of the overlying tissues. When removal is necessary, I evaluate whether the remaining nasal framework needs reconstruction with the patient’s own cartilage.
REVISION RECONSTRUCTION
Rebuilding Nasal Support in Revision Rhinoplasty

When support has been lost or removed during a previous operation, revision rhinoplasty may require more than changing the visible contour of the nose.
I may need to rebuild the underlying framework using cartilage grafts. These grafts can help restore central septal support, reinforce the nasal tip or stabilize areas of weakness along the bridge and nasal sidewalls.
The objective is not simply to create a more attractive shape. It is to create a stable structure capable of supporting that shape over time while addressing functional concerns when possible.
How much reconstruction is needed depends on what remains from the original surgery, the condition of the skin and soft tissue, and the patient’s goals.
RECONSTRUCTIVE OPTIONS
Where Does the Cartilage Come From?
When I need to rebuild nasal support, I may use cartilage from the septum, ear or rib. Each source has different properties, and I choose the graft based on the anatomy I need to reconstruct.
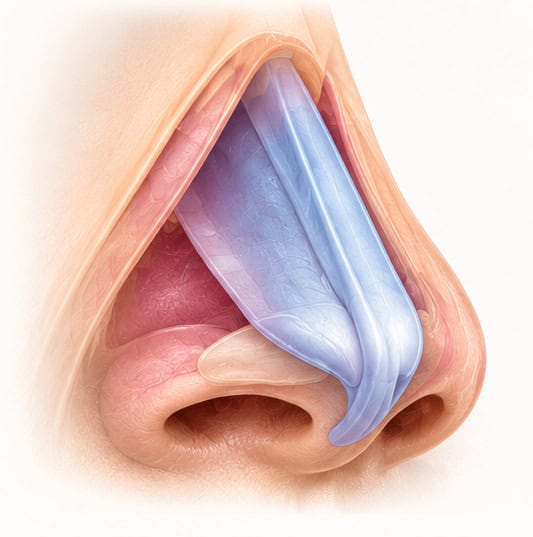
Septum Cartilage
Often my first consideration when enough healthy cartilage remains. It can provide useful structural support without requiring a separate donor site.
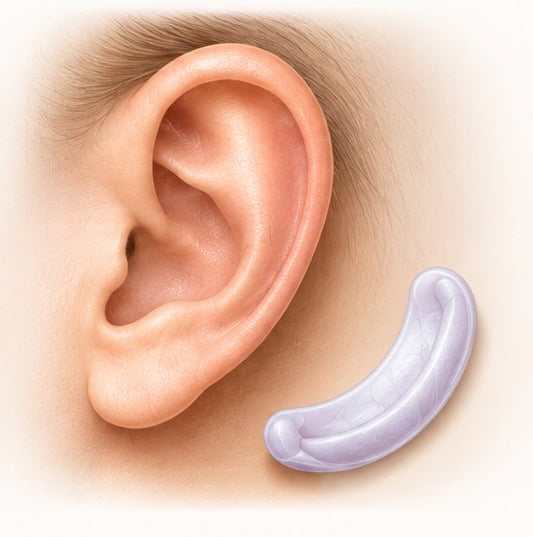
Ear Cartilage
Naturally curved cartilage that can be useful for selected areas of nasal tip and sidewall reconstruction when septal cartilage is insufficient.
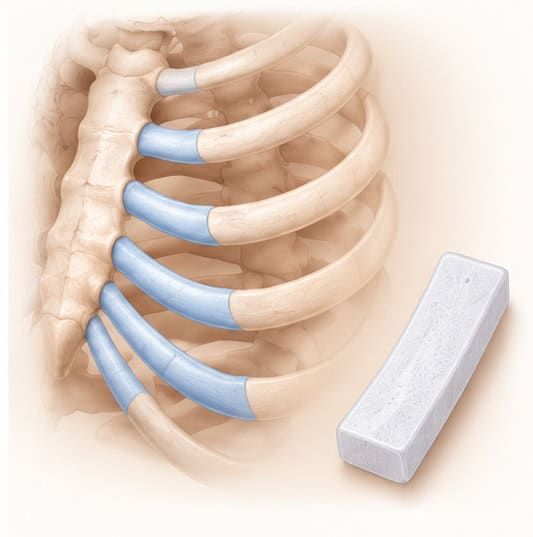
Rib Cartilage
A larger source of strong cartilage that can be valuable when substantial reconstruction is necessary after significant loss of nasal support.
The decision is not simply about which cartilage is strongest. I have to consider how much material is needed, its shape and flexibility, the structures being rebuilt and the additional considerations associated with harvesting cartilage from another part of the body.
WHEN TO CONSIDER REVISION
How Long Should You Wait Before Revision Rhinoplasty?
For most patients, I prefer to wait approximately one year after the original rhinoplasty before deciding on another operation.
That gives swelling time to resolve and scar tissue time to mature. Some noses, particularly those with thicker skin or extensive previous surgery, may continue changing beyond that point.
There are exceptions. Significant breathing problems, infection, implant complications or other concerning changes may need evaluation much sooner.
But an early evaluation does not necessarily mean an early revision. Sometimes my recommendation is simply to continue healing and reassess the result later.
Can Revision Rhinoplasty Fix a Botched Nose Job?
Revision rhinoplasty can improve many problems caused by previous surgery, but the possibilities depend on the anatomy that remains.
Cartilage may be missing. Scar tissue can restrict how the skin and underlying structures move. The nasal lining, blood supply and skin thickness may limit what can safely be accomplished.
Sometimes the priority is restoring breathing and stability. In other cases, the primary concern is the bridge, nasal tip or overall shape. Frequently, both appearance and function need to be addressed together.
I want patients to understand what I believe can be improved, what may remain imperfect and why.
A successful revision is not about promising a perfect nose. It is about understanding what went wrong and making the most appropriate correction the remaining anatomy allows.
When I May Recommend Against Revision Surgery
Not every patient who is unhappy after rhinoplasty will benefit from another operation.
Sometimes the concern is minor and the risks of another surgery outweigh the likely improvement. Sometimes the nose is still healing. And sometimes the result a patient wants is not achievable with the anatomy that remains.
Patients seeking revision surgery may also be dealing with significant disappointment or anxiety following their first experience. I take those concerns seriously, but I have to determine whether surgery can reasonably address the source of their dissatisfaction.
When concerns about appearance are accompanied by disproportionate distress or persistent preoccupation, a more careful evaluation may be appropriate. Body dysmorphic disorder is one consideration, but dissatisfaction after surgery should never automatically be treated as evidence of that condition.
I would rather recommend against another operation than perform surgery when I do not believe it is likely to help.
CHOOSING YOUR SURGEON
How to Choose a Revision Rhinoplasty Surgeon
Revision rhinoplasty is not simply repeating the original procedure. I am often working with anatomy that has already been altered, cartilage that may have been removed, and scar tissue that makes the remaining structures more difficult to identify and reshape. In some cases, the nose must be structurally rebuilt rather than simply refined.
That is why choosing a surgeon with experience in complex revision cases is so important. The surgeon needs to understand how to restore support, address breathing problems, and improve the appearance without compromising what remains of the nasal framework. Just as importantly, they need to recognize what can realistically be accomplished with another operation.
Ask About Revision Experience
Look for a surgeon who regularly evaluates and treats patients who have already undergone rhinoplasty. Revision surgery requires experience with altered anatomy, scar tissue, weakened cartilage, and structural problems that may not be obvious from the outside. A surgeon who primarily performs minor cosmetic refinements may not have the same experience managing noses that require extensive reconstruction.
I would also encourage patients to ask how frequently the surgeon performs revision rhinoplasty and whether they have experience with cases similar to their own. Review before and after photographs of actual revision patients, particularly those who had comparable structural or breathing concerns. The goal is to find someone who can explain what went wrong, how they would approach correcting it, and what limitations may remain.
Understand the Reconstructive Plan
If cartilage grafting is being considered, ask your surgeon where the cartilage will come from and what specific problem it is intended to correct. Cartilage may be taken from the remaining septum, the ear, or the rib, depending on how much support is needed. Each source has different characteristics, and the choice should be based on the structures that need to be rebuilt rather than a surgeon’s preference for one technique.
I also encourage patients to understand how the grafts will be used. Will they reinforce a weakened nasal bridge, restore support to the tip, or help correct a collapsed nasal valve that is affecting breathing? A well-planned revision should have a clear structural purpose for each graft, along with an explanation of the benefits, limitations, and additional risks associated with obtaining the cartilage.
Evaluate Breathing as Well as Appearance
A complete revision rhinoplasty evaluation should consider much more than the external appearance of the nose. I examine the septum, internal and external nasal valves, and the structures that support the airway. A nose can look relatively straight and balanced from the outside while still having significant internal problems that make breathing difficult. Previous surgery may have weakened these structures, even when the changes are not immediately visible.
When choosing a revision surgeon, ask how they evaluate nasal breathing and whether functional problems will be addressed as part of the surgical plan. Improving the appearance of the nose without correcting an underlying airway problem can leave a patient dissatisfied despite a better cosmetic result. My goal is to create a nose that looks natural while preserving or improving its ability to function properly.
Expect an Honest Discussion
A revision consultation should address the likely improvements, limitations, risks and the possibility that some irregularities may remain.
My revision consultations are generally much longer than my primary rhinoplasty consultations because there is more history to review, more anatomy to evaluate and more uncertainty to discuss.
When looking through rhinoplasty before and after photographs, pay attention to the type of operation performed. A primary rhinoplasty result is not equivalent to a complex reconstructive revision.
REVISION RHINOPLASTY PATIENT
Why She Chose Dr. Athré for Revision Rhinoplasty
After researching several surgeons for her revision rhinoplasty, this patient explains what led her to Dr. Athré and what stood out during her experience.
MY SURGICAL APPROACH
How I Approach Revision Rhinoplasty
When a patient comes to me after an unsuccessful rhinoplasty, I start by understanding the original operation and examining the anatomy that remains.
I evaluate the bridge, tip, septum, nasal valves, skin and scar tissue. I also want to understand what the patient hoped to accomplish with the original surgery and what concerns them today.
Some revisions involve a relatively limited correction. Others require extensive structural reconstruction.
If cartilage has been removed, I consider how to restore support. If breathing is compromised, I evaluate the internal structures responsible. If an implant is present, I assess its condition and whether removal or reconstruction is appropriate.
Techniques such as dorsal preservation rhinoplasty and ultrasonic rhinoplasty may be useful in selected circumstances, but they are not substitutes for reconstructing missing support.
For patients traveling to Houston, our out-of-town patient resources explain how we help coordinate the consultation and surgical process.
The operation has to be designed around the nose I am examining, not around a technique or a photograph of someone else’s result.
The goal is not simply to operate again. The goal is to understand the problem well enough to decide whether another operation is the right answer.
BEFORE & AFTER
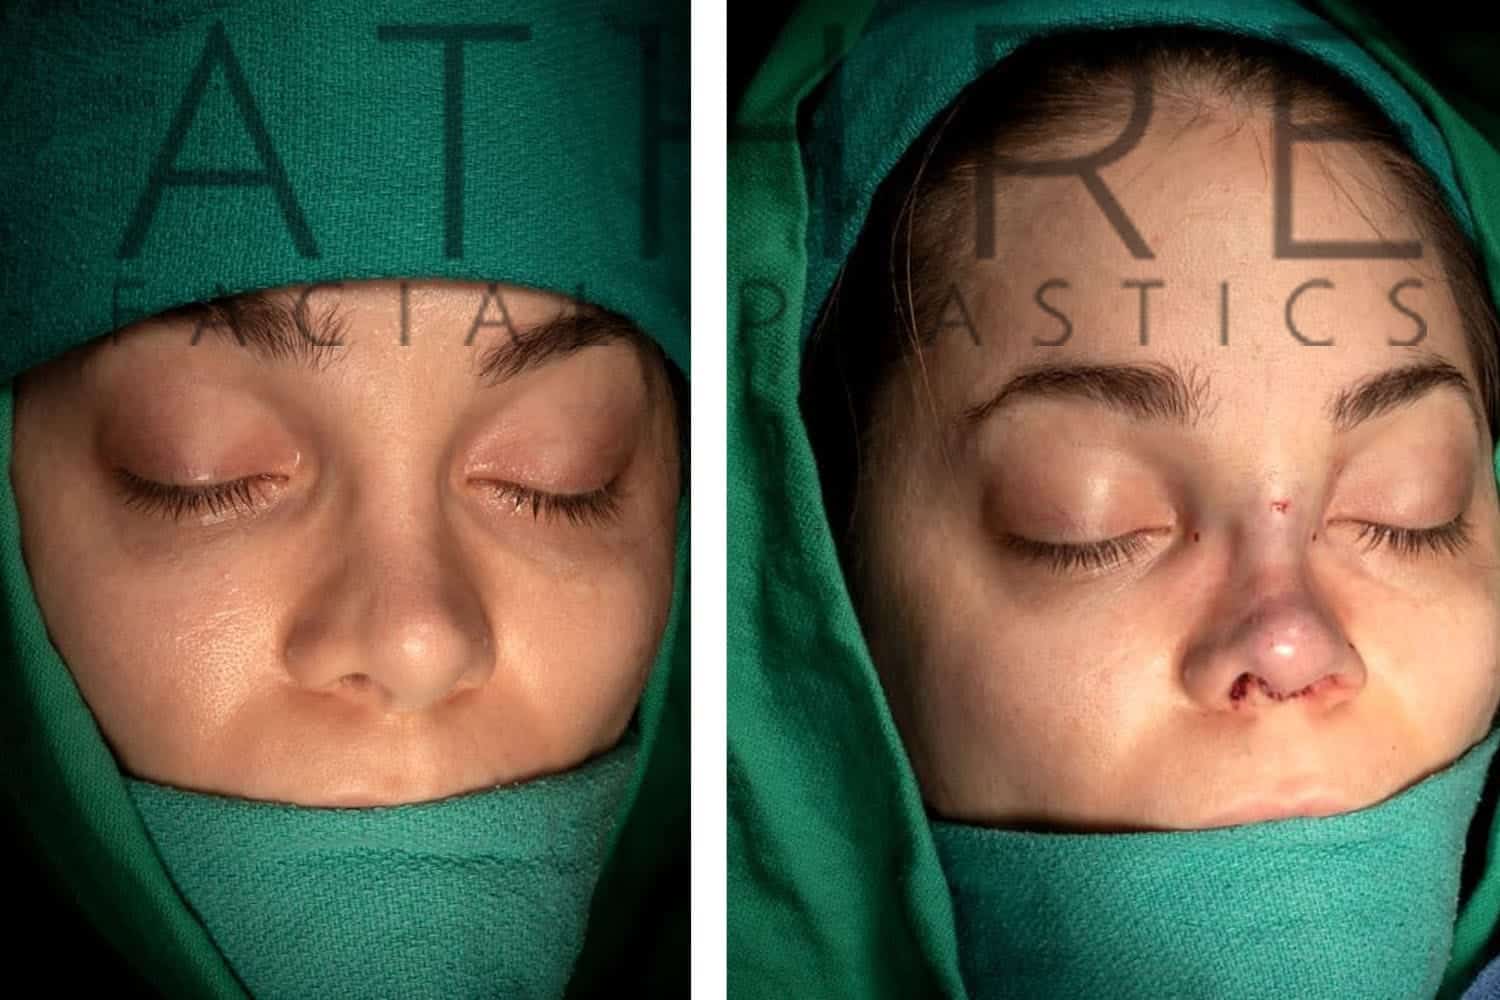
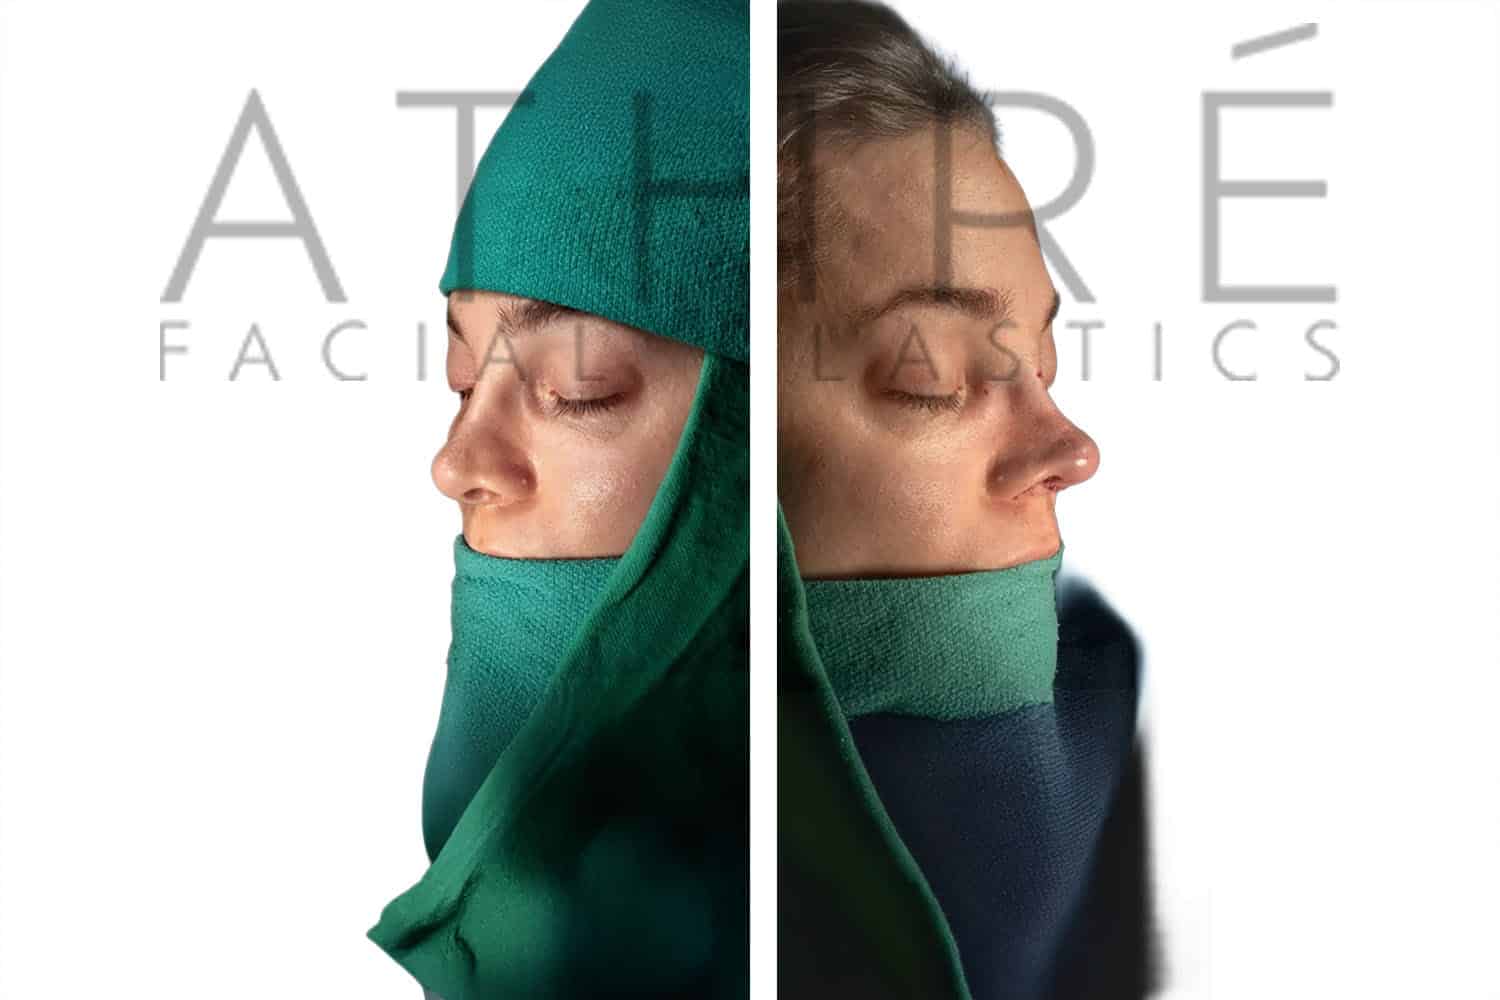
Revision Rhinoplasty Results

FREQUENTLY ASKED
Botched Rhinoplasty FAQs
The most important questions concern whether a problem is temporary, whether the nasal framework is stable and what revision surgery can realistically accomplish.
How common is revision rhinoplasty?
Revision rates vary depending on the patient population, surgical technique and how a revision is defined. Estimates around 5% to 15% are often discussed, but that does not mean exactly one in ten patients will need another operation. A review of published rhinoplasty revision rates helps illustrate why reported figures differ across studies.
How do I know whether my rhinoplasty has failed?
It depends on how long it has been since surgery and whether the concern involves appearance, breathing or both. Early swelling can create asymmetry and contour changes that improve with time. Persistent collapse, nasal obstruction or progressive deformity may suggest a structural problem. Research on functional and aesthetic evaluation in revision rhinoplasty emphasizes examining both the external nose and internal airway.
Can a collapsed nose be repaired after rhinoplasty?
Many forms of nasal collapse can be improved by reconstructing weakened structures with cartilage grafts. The exact technique depends on whether the septum, nasal valves, tip or other supporting structures have been affected. Published research on structural cartilage grafting in revision rhinoplasty describes approaches to restoring nasal support, although the result depends on the remaining anatomy.
Why would I need ear or rib cartilage?
During the first rhinoplasty, some or much of the septal cartilage may already have been removed. When there is not enough healthy cartilage remaining, I may use ear cartilage for selected curved grafts or rib cartilage when larger, stronger grafts are needed. Studies of auricular and costal cartilage grafts in revision rhinoplasty discuss their different reconstructive applications and complications.
Is rib cartilage safe for revision rhinoplasty?
Rib cartilage is an established reconstructive option, particularly when substantial support is needed. However, it introduces considerations such as donor-site discomfort, scarring, graft warping and other surgical risks. Published meta-analyses of costal cartilage graft complications help inform that risk discussion. The decision should be individualized rather than treating rib cartilage as necessary for every revision.
Why is revision rhinoplasty more difficult than primary rhinoplasty?
Previous surgery can leave scar tissue, altered anatomy and reduced cartilage availability. In some patients, important structural elements must be reconstructed rather than simply reshaped. The surgical literature on revision rhinoplasty challenges describes why the operative plan is often more complex than it is in a previously unoperated nose.
How long should I wait before revision rhinoplasty?
In most situations, I recommend allowing approximately 12 months for healing before deciding on revision surgery. Swelling and scar tissue can continue to change during that period. Research measuring postoperative rhinoplasty swelling over the first year supports the importance of allowing time for the result to mature. Significant breathing problems or other complications may warrant evaluation sooner.
Can revision rhinoplasty guarantee the result I originally wanted?
No. Revision rhinoplasty can improve many structural, functional and cosmetic problems, but the remaining cartilage, scar tissue, skin and healing response all influence the outcome. Research on patient-reported outcomes after revision rhinoplasty can help explain the potential for improvement, but no published average can guarantee an individual result.